For small and mid-sized pharmaceutical and biotech companies, “affordable clinical research” should not mean simply finding the lowest rate card. The largest savings often come from somewhere else: avoiding unnecessary complexity, reducing rework, applying controls proportionately, and using technology only…
Clinical research generates a large amount of data: protocol-defined assessments, CRF data, laboratory results, adverse events, exposure records, endpoint data, statistical analysis datasets, tables, listings, figures, metadata, and regulatory submission packages. Without standards, every sponsor, CRO, vendor, and system may…
How does a CRO interact with a sponsor? What is project-based delivery, what is FSP, and what hybrid models sit between them? What do the evidence – and real delivery practice – suggest for biometrics teams? In clinical development, outsourcing…
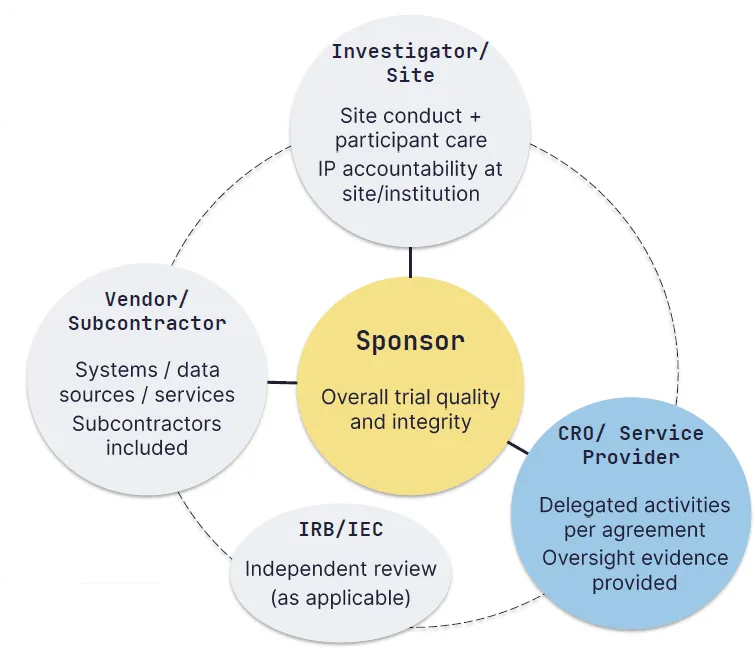
We’re closing our E6(R3) series with two principles that most often decide whether execution stays clean: role clarity and IP/blinding traceability. 10) Roles and responsibilities (clarity + oversight) Key roles, interfaces, and responsibilities should be clearly defined and documented appropriately…
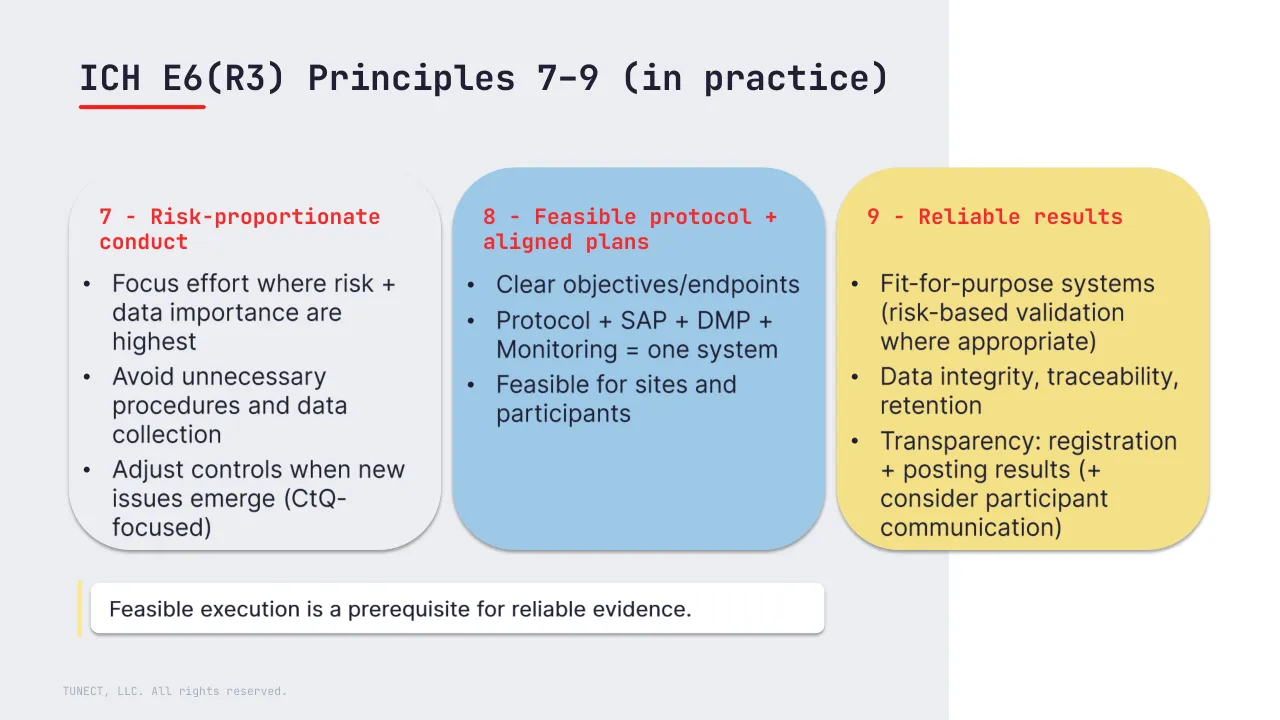
Now we move from design principles to making execution feasible and ensuring the results are reliable. 7) Risk-proportionate trial conduct (avoid unnecessary burden) Processes should be proportionate to risks to participants (including risks beyond usual care where relevant) and to…
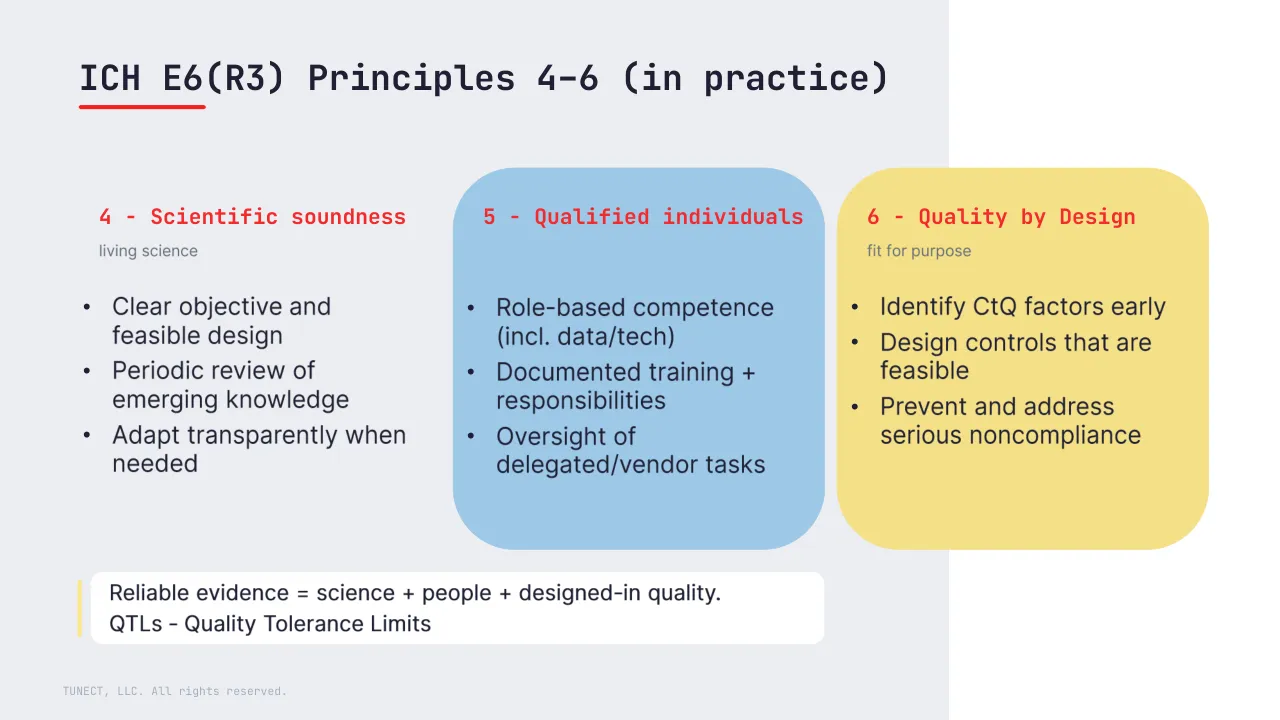
In the last post we covered Principles 1-3 (ethics, consent, independent review). Now we move to the reliability backbone of trial evidence: science, people, and quality by design. 4) Scientifically sound trials (and periodic review) Trials should be scientifically sound…
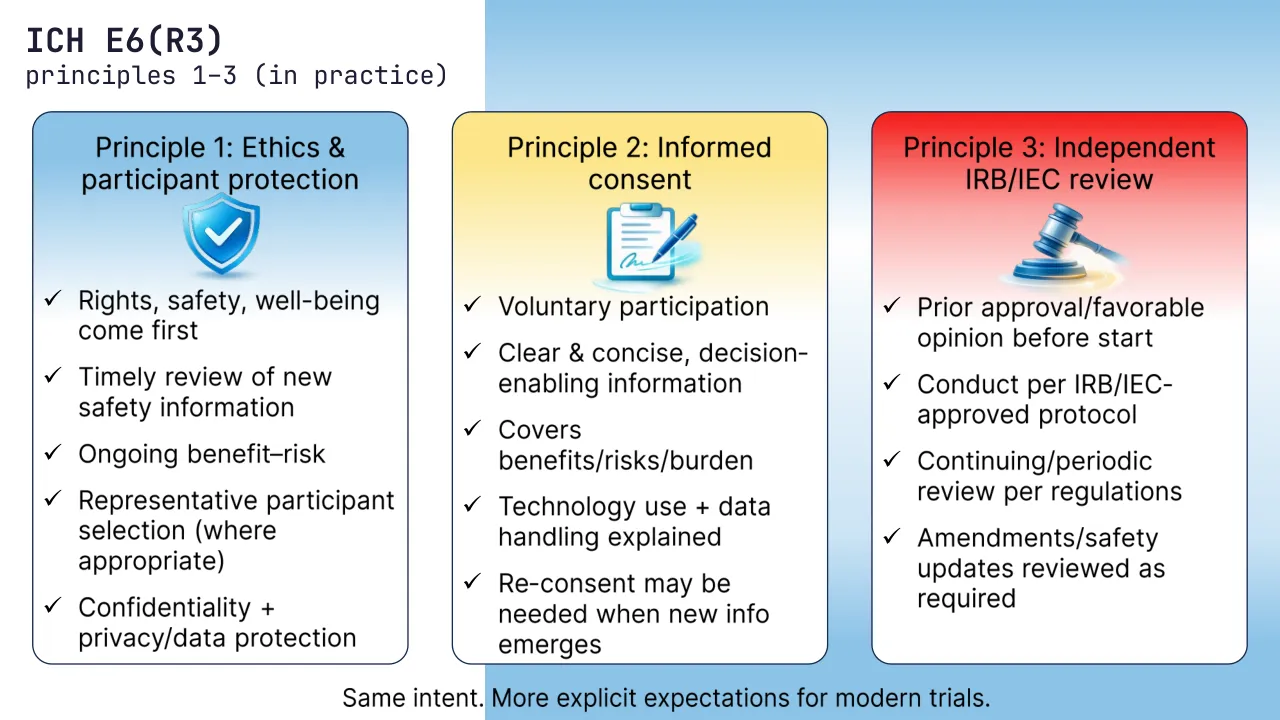
We’re starting the series on the 11 principles of ICH E6(R3). E6(R3) consolidates and reframes the 13 principles from E6(R2) into 11 with clearer emphasis and more practical expectations. 1) Ethical conduct and participant protection (Declaration of Helsinki) Clinical trials…